
Retatrutide comparisons
A quick orientation: what’s actually approved
Before comparing efficacy figures, it’s worth being clear about where each compound sits in the regulatory picture, since this changes what kind of evidence is even available.
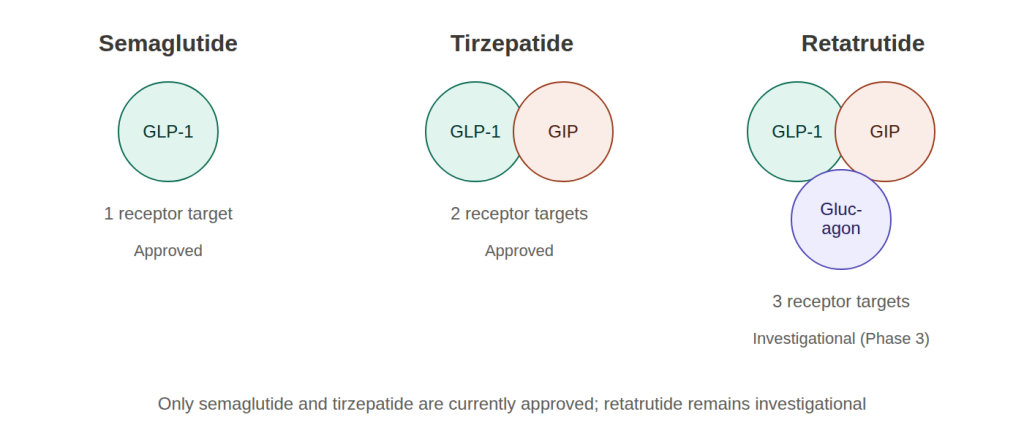
| Compound | Receptor targets | UK/US regulatory status |
|---|---|---|
| Semaglutide | GLP-1 | Approved (Ozempic, Wegovy) |
| Tirzepatide | GLP-1, GIP | Approved (Mounjaro, Zepbound) |
| Retatrutide | GLP-1, GIP, glucagon | Investigational — Phase 3 trials ongoing |
Only semaglutide and tirzepatide currently have full peer-reviewed, real-world post-approval datasets behind them. Retatrutide’s evidence base, while substantial, still consists primarily of trial data rather than years of prescribing experience.
Researchers and readers should therefore interpret emerging findings within the context of the available evidence and recognize the distinction between controlled clinical trial outcomes and long-term real-world data. For a deeper examination of the compound’s development, mechanisms, and current research landscape, see our detailed guide to Retatrutide research.
Retatrutide vs Tirzepatide
Mechanism difference
Tirzepatide is a dual agonist, activating GLP-1 and GIP receptors. Retatrutide adds a third target — the glucagon receptor — which researchers believe is responsible for its additional effects on energy expenditure and liver fat that aren’t seen to the same degree with dual-agonist compounds.
What the trial data shows
| Measure | Retatrutide (TRIUMPH-4, 12mg) | Tirzepatide (SURMOUNT-1, 15mg) |
|---|---|---|
| Trial duration | 68 weeks | 72 weeks |
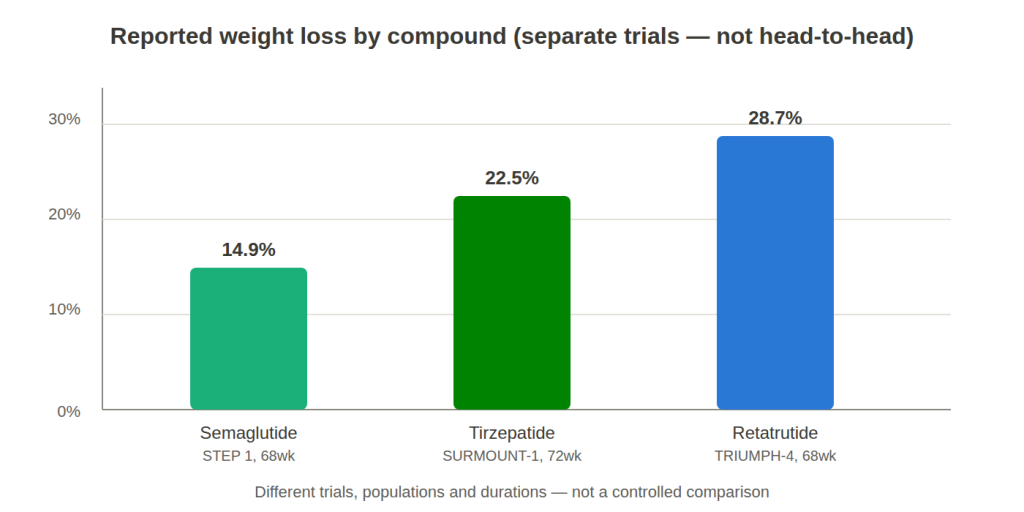
| Reported weight loss | ~28.7% | ~22.5% |
| Population | Obesity + knee osteoarthritis | Obesity or overweight |
| Regulatory stage at time of data | Phase 3 topline | Approved, post-market data available |
Important caveat: no head-to-head trial directly comparing retatrutide against tirzepatide has yet been published. The figures above come from separate trials with different populations, durations and designs — a cross-trial comparison, not a controlled comparison. Treat the gap between them as suggestive, not conclusive, until a dedicated comparator trial reports.
Retatrutide vs Semaglutide
Mechanism difference
Semaglutide is a single-receptor GLP-1 agonist — the most established and extensively studied mechanism in this drug class. Retatrutide’s additional GIP and glucagon receptor activity is the basis for its larger reported weight-loss signal, though this also means it’s a mechanistically newer and less real-world-tested approach.
What the trial data shows
| Measure | Retatrutide (TRIUMPH-1, 12mg) | Semaglutide (STEP 1, 2.4mg) |
|---|---|---|
| Trial duration | 80 weeks | 68 weeks |
| Reported weight loss | ~25.0% | ~14.9% |
[IMAGE 2 — CHART: retatrutide-semaglutide-tirzepatide-comparison-bar-chart — grouped bar chart of reported weight loss by compound and trial]
Why the size of this gap should be read cautiously
A near-doubling of reported weight loss looks dramatic on paper, but semaglutide’s figures come from years of trials plus post-market surveillance across millions of patients — a depth of evidence retatrutide doesn’t yet have. Novel compounds in Phase 3 often show striking early numbers that moderate somewhat once broader, longer-term and more diverse trial populations are studied.
When reviewing these differences, it is important to understand how clinical evidence is generated, compared, and interpreted. Our research education resources on evaluating peptide studies, trial data, and scientific evidence quality provide further guidance on reading study results with appropriate context rather than focusing only on headline figures. Research Guides and Education offers additional background on research methodology, analytical verification, and evidence evaluation.
The one genuine head-to-head data point in this space: tirzepatide vs semaglutide
While no head-to-head trial yet exists for retatrutide, one does exist comparing tirzepatide directly against semaglutide — and it’s worth including here because it demonstrates what a properly controlled comparison actually looks like, in contrast to the cross-trial comparisons above.
The SURMOUNT-5 trial, a randomised, open-label, active-comparator Phase 3b study of 751 adults with obesity, directly randomised participants to tirzepatide or semaglutide rather than comparing separate trials. Published in the New England Journal of Medicine, it found tirzepatide produced a mean weight reduction of 20.2% compared with 13.7% for semaglutide at 72 weeks — a statistically significant difference (p<0.001), with tirzepatide also showing greater improvements in blood pressure, HbA1c and lipid measures. This is the standard of evidence a retatrutide-vs-tirzepatide comparison would need to move from “suggestive” to “confirmed.”
Retatrutide vs Other Research Compounds
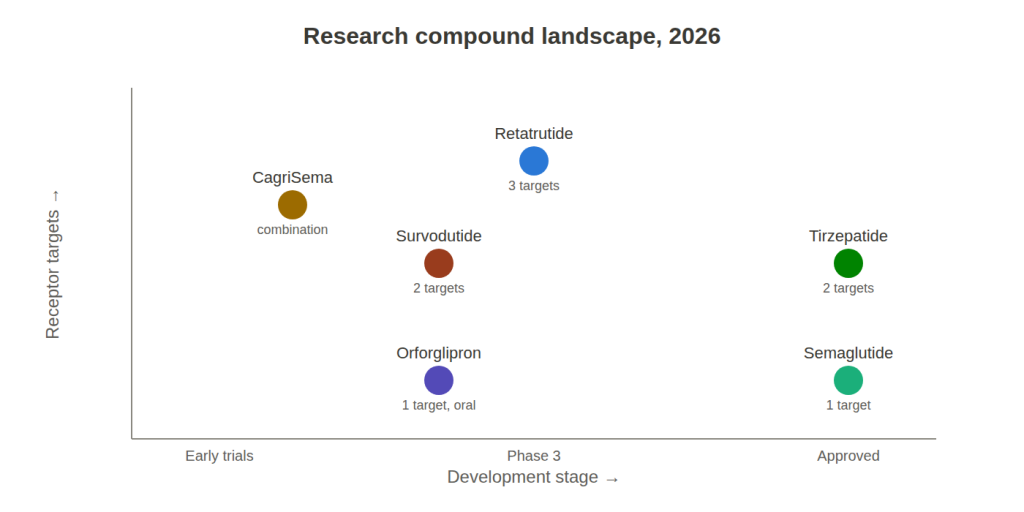
Beyond the three headline molecules, several other compounds occupy the same research space:
- Orforglipron — an oral (non-injectable) GLP-1 receptor agonist, notable for being small-molecule rather than peptide-based, which simplifies manufacturing and administration in trials.
- Survodutide — a GLP-1/glucagon dual agonist, sharing retatrutide’s glucagon-receptor mechanism without the added GIP activity.
- CagriSema — a combination of semaglutide with cagrilintide (an amylin analogue), representing a different combination strategy — pairing compounds rather than building multi-receptor agonism into one molecule.
Retatrutide remains the most clinically advanced triple-receptor agonist among this group, giving it the largest published dataset of any non-approved multi-agonist candidate as of mid-2026.
Frequently Asked Questions
Is retatrutide better than tirzepatide?
No trial has directly compared them yet, so this can’t be answered with confidence. Cross-trial figures suggest a larger reported effect for retatrutide, but different trial populations and designs make this an unreliable basis for a direct claim.
Is retatrutide better than semaglutide?
Similarly unconfirmed by head-to-head data. Reported weight-loss figures are notably higher for retatrutide in separate trials, but semaglutide has a much larger and longer-established evidence base overall.
Why don’t we have head-to-head retatrutide trials yet?
Head-to-head active-comparator trials are typically run later in a compound’s development, once initial placebo-controlled Phase 3 data is established — this is the pattern seen with tirzepatide, whose head-to-head SURMOUNT-5 comparison against semaglutide came several years after its initial approval.
What other compounds are being researched in this space?
Orforglipron (an oral GLP-1 agonist), survodutide (a GLP-1/glucagon dual agonist), and CagriSema (a semaglutide-cagrilintide combination) are among the other notable candidates in active development.
[IMAGE 3 — DIAGRAM: research-compound-landscape-2026 — simple map of compounds by receptor target and development stage]
Conclusion
The honest summary of where this comparison stands in mid-2026: retatrutide’s separate-trial figures look larger than tirzepatide’s and considerably larger than semaglutide’s, but “looks larger in separate trials” and “proven superior in a head-to-head trial” are different evidentiary standards — and only the SURMOUNT-5 tirzepatide-vs-semaglutide comparison currently meets the second bar. Until a genuine active-comparator trial involving retatrutide reports, any ranking between the three should be treated as a working hypothesis based on the available data, not a settled conclusion.
External source embedded above: SURMOUNT-5 results, published in the New England Journal of Medicine — summarised via the American College of Cardiology’s journal scan.